Scarring alopecia: diagnosis and treatment
Scarring alopecia describes conditions that damage hair follicles and replace them with scar tissue. An assessment by a dermatologist is important because treatment aims to control the condition and protect the hair that remains.

Scarring alopecia explained: a UK patient guide

What is scarring alopecia, and how does it differ from other hair loss?
Scarring alopecia, also known as cicatricial alopecia, is a group of disorders in which hair follicles are irreversibly destroyed and replaced by scar tissue, resulting in permanent hair loss. Unlike non-scarring alopecia, where the follicle remains structurally intact and regrowth is possible, scarring alopecia closes off any prospect of natural recovery in the affected area. That distinction is clinically critical and shapes every decision that follows.
The condition is divided into two broad classes. Primary scarring alopecia targets the follicle directly, with inflammation attacking the epithelial stem cells in the hair follicle bulge. Secondary scarring alopecia arises when follicle destruction is a consequence of another process altogether, such as burns, radiation, or severe infection. Within the primary class, subtypes are grouped by the dominant inflammatory cell type: lymphocytic, neutrophilic, or mixed. The two most common forms are lichen planopilaris (LPP) and frontal fibrosing alopecia (FFA), both of which predominantly affect women.
Key points at a glance:
- Follicle destruction is permanent; lost follicles cannot be regenerated by any current treatment.
- Primary cicatricial alopecia is classified as lymphocytic, neutrophilic, or mixed.
- LPP and FFA are the most prevalent types in the UK.
- Non-scarring alopecia (e.g., alopecia areata, telogen effluvium) leaves follicles intact and carries potential for regrowth.
- The Primary Care Dermatology Society (PCDS) classifies scarring alopecia as irreversible, making early referral a priority.
Table of Contents
- How is scarring alopecia diagnosed in the UK?
- What symptoms should you look out for?
- What treatment options are available for scarring alopecia in the UK?
- How should you manage scarring alopecia over the long term?
- What hair restoration options are available once the condition is stable?
- Key takeaways
- FAQ
How is scarring alopecia diagnosed in the UK?
Distinguishing scarring from non-scarring alopecia is the single most important step in clinical assessment, because the management pathway diverges entirely at that point. A clinician examining the scalp will look for the loss of follicular ostia (the small openings through which hairs emerge), a shiny or atrophic surface, and any perifollicular inflammation or pigmentary change. These signs point strongly toward a scarring process.
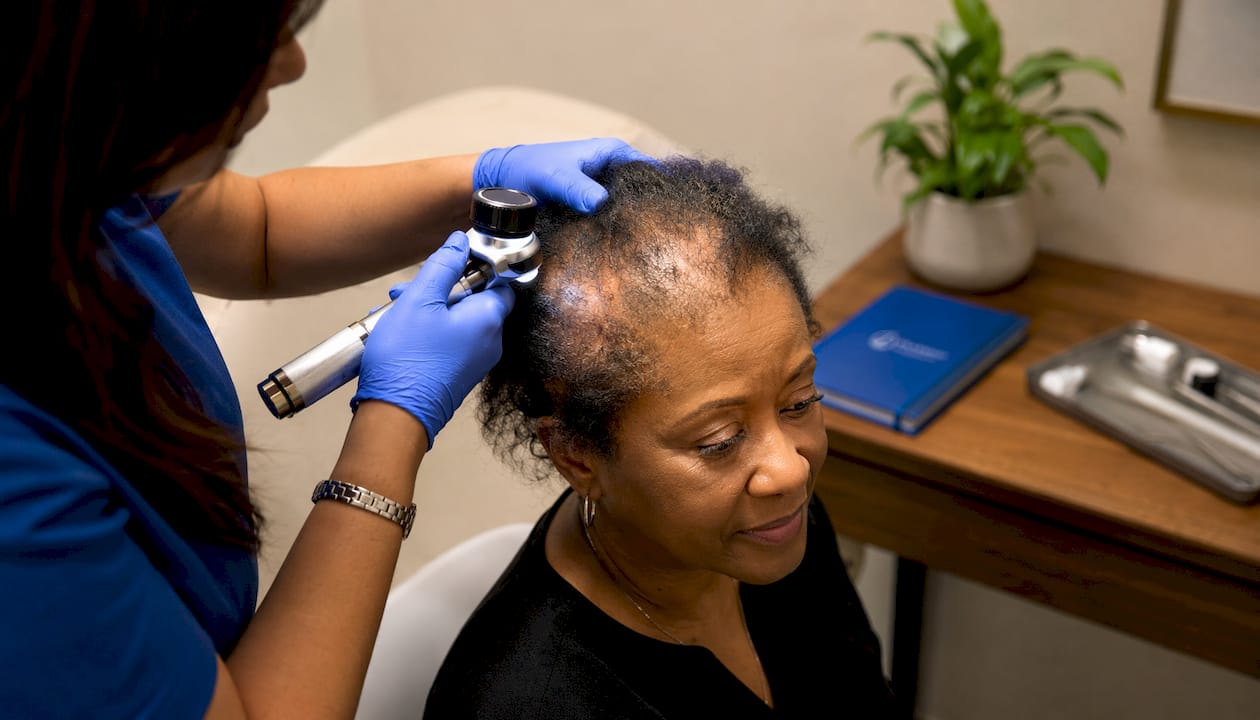
Dermoscopy has become an indispensable tool at this stage. It can reveal the absence of follicular openings, atrophic skin, and tufting patterns such as “dolls hair” tufting, where multiple hairs emerge from a single follicular unit as surrounding follicles are destroyed. Dermoscopic findings guide the urgency of onward referral and help clinicians at EIV Diagnostics and similar dermatopathology services prepare for targeted biopsy analysis.

A scalp biopsy remains the gold standard for confirming the diagnosis and identifying the specific subtype. Patients with suspected scarring alopecia in the UK require urgent dermatology referral to minimise further permanent loss. In primary care, a blood screen is typically arranged before that referral.
Diagnostic steps summarised:
- Clinical examination for loss of follicular ostia, shiny or atrophic scalp, and perifollicular inflammation.
- Dermoscopy to detect tufting, absent follicular openings, and skin texture changes.
- Scalp biopsy for definitive subtype confirmation.
- Blood tests in primary care: FBC, U&E, LFT, ferritin, TFT, and ANA.
- Urgent dermatology referral once scarring alopecia is suspected.
What symptoms should you look out for?
Symptoms of scarring alopecia vary considerably between patients and between subtypes. Some people experience significant discomfort; others notice nothing beyond progressive hair loss. That variability makes the condition easy to underestimate.
Common symptoms include:
- Itching, burning, pain, or altered sensation on the scalp.
- Patchy or diffuse hair loss, often with a shiny, smooth surface where hair has been lost.
- Perifollicular scaling or redness in active phases.
- Tufting of hairs in affected areas.
Crucially, inflammation may be entirely subclinical, meaning the disease can be actively destroying follicles beneath the skin surface with no visible redness or swelling. Patients who feel no symptoms should not assume their condition is stable. FFA, for example, is asymptomatic in the majority of cases, with only around a quarter of patients reporting itching or pain in the affected hairline area. Regular clinical monitoring is the only reliable way to assess activity.
What treatment options are available for scarring alopecia in the UK?
The goal of treatment is unambiguous: stop further follicle destruction. No current therapy can restore follicles that have already been lost. Early intervention therefore carries far more weight than it does in non-scarring conditions, where a delayed start still leaves regrowth possible.
Medical management draws on several drug classes, each targeting the inflammatory process through a different mechanism:
- Topical and intralesional corticosteroids: First-line agents applied directly to active areas to suppress localised inflammation.
- Calcineurin inhibitors (e.g., tacrolimus): Used where steroids are not tolerated or as adjuncts.
- Tetracycline antibiotics (e.g., doxycycline): Prescribed for their anti-inflammatory properties rather than antimicrobial action, typically for six months before response is assessed.
- Oral hydroxychloroquine: Commonly used in lymphocytic subtypes such as LPP and FFA; trialled over 4–6 months with monitoring including annual eye examinations for retinal toxicity.
- Immunosuppressants (e.g., ciclosporin, methotrexate): Reserved for refractory cases; require close monitoring with regular blood tests.
For patients exploring hair loss medication options alongside specialist care, understanding which drug class applies to their specific subtype is an important first conversation with their dermatologist.
How should you manage scarring alopecia over the long term?
Scarring alopecia is a chronic condition. Achieving disease stability is not a one-time event; it requires sustained monitoring and, for many patients, ongoing treatment adjustments over years. Patients should expect regular clinic visits, periodic blood tests, and surveillance for medication side effects.
Hydroxychloroquine in particular carries a risk of retinal toxicity with long-term use, making annual eye examinations non-negotiable. Immunosuppressants require blood monitoring to detect hepatic or haematological changes before they become clinically significant.
Beyond pharmacological management, the psychosocial burden of permanent hair loss is real and should be addressed directly. Referral to psychological support services or counselling is appropriate for many patients. Optimising diet, maintaining micronutrients within reference range, and adopting a gentle scalp care routine all contribute to the overall management plan. Organisations such as Alopecia UK provide peer support and guidance on cosmetic camouflage options that can be just as meaningful as active treatment for day-to-day wellbeing.
Long-term monitoring checklist:
- Regular dermatology follow-up to assess disease activity.
- Annual eye examinations for patients on hydroxychloroquine.
- Periodic blood tests for patients on immunosuppressants.
- Psychological support referral where appropriate.
- Dietary optimisation, aiming for micronutrients at mid-reference range or above.
What hair restoration options are available once the condition is stable?
Hair restoration after scarring alopecia is possible, but the timing and approach require careful clinical judgement. Hair transplant surgery is generally deferred until the inflammatory process has been well-controlled for an extended period, typically several years. Proceeding during active disease carries a high risk of graft failure and potential exacerbation of the underlying condition.
When disease inactivity is confirmed, surgical restoration becomes a realistic option for suitable patients. The procedure involves transplanting follicular units from a healthy donor area into the scarred region, a technically demanding process given the altered tissue environment. Patients with conditions such as CCCA should also be aware of an elevated risk of keloid scar formation.
While awaiting surgical eligibility, or for those who prefer non-surgical routes, several options provide meaningful cosmetic benefit:
- Scalp micropigmentation (SMP): A non-surgical technique that replicates the appearance of hair follicles using specialised pigment, creating the look of a closely cropped scalp.
- Wigs and hairpieces: High-quality options that can be prescribed through NHS dermatology services in cases of significant psychological distress.
- Cosmetic camouflage products: Fibres, sprays, and concealers that reduce the visual contrast between hair and scalp.
Glasgowhairtransplantclinics offers a full range of hair restoration services across the UK, with GMC-registered surgeons and CQC-registered clinics. Whether you are exploring hairline transplant options or scalp micropigmentation, the team provides personalised consultations to assess your suitability and set realistic expectations. A free online or face-to-face consultation is available to help you understand your options before committing to any procedure.
Pro Tip: If you have been diagnosed with a scarring alopecia subtype, ask your dermatologist for a written record of disease activity at each visit. This documentation becomes essential when assessing surgical eligibility later.
Key takeaways
Scarring alopecia requires early diagnosis and sustained treatment to halt follicle destruction, as lost follicles cannot be restored by any current medical or surgical intervention.
| Point | Details |
|---|---|
| Permanent follicle loss | Destroyed follicles cannot regenerate; the treatment goal is to stop further loss, not reverse it. |
| Urgent referral matters | UK patients with suspected scarring alopecia need urgent dermatology referral to minimise irreversible damage. |
| Subclinical inflammation | Absence of visible redness does not confirm disease inactivity; monitoring remains necessary. |
| Treatment timelines | Hydroxychloroquine is trialled over 4–6 months; tetracycline antibiotics are typically assessed after six months. |
| Surgery requires stability | Hair transplant surgery is deferred until inflammation has been inactive for several years to reduce graft failure risk. |
FAQ
What is the difference between scarring and non-scarring alopecia?
Scarring alopecia permanently destroys hair follicles and replaces them with scar tissue, making hair loss irreversible. Non-scarring alopecia leaves follicles intact, so regrowth remains possible with appropriate treatment.
Can scarring alopecia be cured?
There is currently no cure for scarring alopecia. Treatment focuses on halting disease progression and preserving remaining hair through anti-inflammatory therapies.
How is scarring alopecia diagnosed?
Diagnosis involves clinical examination, dermoscopy to detect absent follicular openings and tufting patterns, a scalp biopsy for subtype confirmation, and blood tests including FBC, ferritin, TFT, and ANA.
Is a hair transplant possible if you have scarring alopecia?
A hair transplant may be considered once the inflammatory process has been well-controlled for several years, but it carries a higher risk of failure than standard transplantation and requires thorough specialist assessment beforehand.
What types of scarring alopecia are most common in the UK?
Lichen planopilaris (LPP) and frontal fibrosing alopecia (FFA) are the two most prevalent types, both classified as lymphocytic primary cicatricial alopecias and most commonly affecting women.
Recommended
When to have your scalp checked
Arrange medical advice for unexplained patches of loss, especially if the scalp is sore, burning, itchy, red or scaly. Some affected areas look smooth or shiny. Symptoms can be mild, and photographs alone may not distinguish scarring from other causes.
A dermatologist may examine the scalp with magnification and recommend a biopsy if the diagnosis is uncertain. The pattern, symptoms and medical history help determine which investigations are useful.
Why the diagnosis matters
Scarring alopecia is a group of disorders rather than one disease. Lichen planopilaris is one example. The British Association of Dermatologists explains that it can destroy follicles and cause permanent loss. Treatment may control symptoms and disease activity, but cannot be relied on to regrow hair where follicles have been destroyed.
Different conditions require different treatment plans. Do not start a prescription treatment from a photograph or another patient’s experience. Ask how the diagnosis will be monitored and what side effects to watch for.
Can a transplant help?
A transplant is not the first step while an inflammatory condition is active. In selected cases, surgery may be discussed after sustained stability and specialist assessment. The condition can recur and affect transplanted hair, so a quiet-looking scalp does not guarantee a lasting result.
Ask the dermatologist and surgeon how they will judge stability, what evidence supports surgery in your case and what follow-up would be needed.
Support and appearance
Wigs, hairpieces and camouflage products may help while treatment is being considered or if surgery is unsuitable. Ask about options that will not irritate your scalp or pull on remaining hair.
If you have unexplained loss or scalp symptoms, start with your GP. A cosmetic consultation can follow once the diagnosis and treatment priorities are clear.
Contact our Belfast team
Consultations are by appointment at Regus, Forsyth House, Cromac Street, Belfast BT2 8LA. Arrange a consultation or call 028 9600 0113. We will confirm the appointment details before you travel.
Questions and answers
Why does scarring alopecia need a diagnosis before restoration is considered?
The cause and whether it is active affect the treatment plan. A clinician may need to investigate inflammation or other scalp changes before discussing surgery.
Does a smooth patch prove that the condition has stopped?
No. Appearance alone cannot establish whether a scarring condition is inactive. Explain any itching, pain, redness or recent change, and follow the assessment advised by your clinician.
Can a transplant treat the underlying scarring condition?
A transplant does not treat the inflammatory disease itself. If surgery is considered, the surgeon must assess disease activity, the scarred scalp and the limitations on growth and further hair loss. The British Association of Dermatologists’ lichen planopilaris leaflet explains one form of scarring alopecia and its treatment limitations.